


Podcast: Play in new window | Download
My name is Patrik Hutzel from intensivecareathome.com, where we provide tailor-made solutions for long-term ventilated adults and children at home with tracheostomies with 24/7 ICU and critical care trained nurses, where we provide tailor-made solutions at home for long-term ventilated adults and children on BiPAP (Bilevel Positive Airway Pressure), CPAP (Continuous Positive Airway Pressure) without tracheostomy with 24-hour critical care registered nurses, where we provide tailor-made solutions for tracheostomy adults and children at home without ventilation with 24-hour intensive care nurses at home.
We also provide home ventilation and tracheostomy weaning whenever medically appropriate, home cough assist management, home TPN (Total Parenteral Nutrition), home IV (intravenous) fluids, IV antibiotics, IV potassium, IV magnesium, as well as other electrolyte infusions. We provide central line, PICC (Peripherally Inserted Central Catheter) line, Hickman’s line and port management at home, as well as IDC (Indwelling Catheter), SPC (Suprapubic Catheter), PEG (Percutaneous Endoscopic Gastrostomy) and PEJ (Percutaneous Endoscopic Jejunostomy) tube, nasogastric tube and nasojejunostomy tube management at home. We also provide palliative care services at home, and we provide Level 2 and Level 3 NDIS (National Disability Insurance Scheme) support coordination, as well as TAC (Transport Accident Commission) and WorkSafe case management.
In today’s video blog, I want to answer a question from a mother whose newborn daughter has been on a ventilator since birth. Here is what she actually wrote to me:
“Hi Patrik,
My baby has been on a ventilator since birth because of meconium aspiration, and it’s now day 38. Now the ICU doctors say they will perform a tracheostomy. My baby is a full-term baby. Is it safe, will it affect her in the future, and can we go home with Intensive Care at Home even with a tracheostomy?”
First of all, I am very sorry you’re going through this. 38 days in a neonatal or pediatric intensive care unit is a long time for any family, especially with a newborn baby. And when the doctors start talking about a tracheostomy, it can feel like the ground is moving under your feet. Let’s break this down step by step, so you can go into your next family meeting with the intensive care team informed, confident and with solutions, especially since you want to go home with Intensive Care at Home.
And if you need help right now, if your baby is in NICU (Neonatal Intensive Care Unit) or PICU (Pediatric Intensive Care Unit) and the team is talking about a tracheostomy or long-term ventilation, talk to us about what going home can look like with Intensive Care at Home. Call us at intensivecareathome.com, or book a call with me by clicking on the schedule appointment button, or send me an email to [email protected].
And before we go on to what meconium aspiration syndrome is, you might also be wondering what makes me qualified to answer questions like this for families in intensive care, whether it’s adult or pediatric ICU. Well, I have worked in critical care nursing for over 25 years in three different countries, where I worked as a nurse manager for over 5 years in intensive care, and I started Intensive Care at Home in 2012 in Australia. That’s how long we’ve been operating for. And I was also part of pioneering Intensive Care at Home services in the early 2000s in Germany, with a service at the time called Brambring Jaschke in Munich. Big shout out to Jörg and Kristoff, by the way. And that’s why I brought the concept to Australia in 2012, and like I said, that’s how long we’ve been operating in Australia for.
And I also run a consulting and advocacy service for families in intensive care at intensivecarehotline.com. You can check out our sister site there.
So let’s now look at what meconium aspiration syndrome is. Meconium is your baby’s very first stool. Sometimes a baby passes meconium before or during birth and then breathes that meconium-stained fluid into the lungs. This is called meconium aspiration syndrome, or MAS (Meconium Aspiration Syndrome).
Meconium in the lungs can cause several problems at once:
- It can partially or fully block the small airways.
- It causes a chemical inflammation of the lung tissue, also known as a chemical pneumonitis.
- It interferes with surfactant, the substance that keeps the tiny air sacs in the lungs open.
- It is often linked to PPHN (Persistent Pulmonary Hypertension of the Newborn), where the blood vessels in the lungs stay tight and blood doesn’t flow through the lungs properly to pick up oxygen.
That’s why some babies with MAS need a ventilator, high-frequency ventilation, nitric oxide, and in the most severe cases, even ECMO (Extracorporeal Membrane Oxygenation).
So why is my baby still on a ventilator at day 38? Here’s something really important to understand. Many babies with meconium aspiration syndrome improve over days to a couple of weeks. When a full-term baby is still ventilated at day 38, the question you need to ask the team is, “What exactly is keeping my baby on the ventilator right now?”
Possible reasons can include:
- Ongoing pulmonary hypertension that hasn’t fully settled.
- Lung injury or chronic lung changes after weeks of ventilation.
- Airway problems from a long time with a breathing tube, such as narrowing below the vocal cords, subglottic stenosis, or a soft, floppy airway, known as tracheomalacia.
- Weakness or deconditioning after weeks of sedation and ventilation.
- A neurological injury. For example, if your baby didn’t get enough oxygen around the time of birth, which can affect breathing drive, swallowing or airway protection.
- Repeated failed attempts to take the breathing tube out, failed extubations.
- Infections such as VAP (Ventilator-Associated Pneumonia).
I’m not your baby’s doctor, and I can’t tell you which of these applies to your daughter. But knowing the why is critical, because the reason your baby is still ventilated is what will most likely determine her future, much more than the tracheostomy itself.
So why do ICU doctors recommend a tracheostomy for a baby? When a baby or a child needs breathing support for a long time, a breathing tube through the mouth or nose, an endotracheal tube, becomes less and less suitable. A tracheostomy is a small surgical opening in the front of the neck into the windpipe, with a small tube placed into it. Common reasons the team may recommend a tracheostomy include:
- Protecting the airway. A long time with an endotracheal tube can damage the voice box and the windpipe.
- A more secure airway. A tracheostomy tube is generally speaking easier to secure and manage long term.
- Less sedation. Your baby can be more awake, held, cuddled and able to interact.
- Development. Being awake and more mobile helps with development, play and bonding.
- Weaning. It can make it easier to gradually wean off the ventilator at your baby’s own pace.
- And coming back to your original question, going home. It can open the door to going home with Intensive Care at Home, even if your baby still needs a ventilator for a while.
When you look at the evidence on our website at intensivecareathome.com, we publish the evidence-based Mechanical Home Ventilation Guidelines. They also list indications for invasive ventilation with tracheostomy, including failure to transfer to non-invasive ventilation, such as mask ventilation, after invasive ventilation; ineffective management of secretions; and when non-invasive ventilation is ineffective or not tolerated. For infants in particular, masks often don’t fit well, so non-invasive ventilation isn’t always an option.
Is a tracheostomy safe for a newborn baby? Let me be clear with you, because that’s what you deserve. A tracheostomy requires surgery, and no surgery is completely risk-free. Possible risks include bleeding, infection, problems in the first days while the stoma, the opening, heals, a blocked tube, and the tube accidentally coming out, which is known as an accidental decannulation.
With babies, there are some extra considerations. Again, our evidence-based mechanical home ventilation guidelines on our website at intensivecareathome.com highlight that, for example:
- The smaller the tracheostomy tube, the higher the risk of it blocking with secretions. Even a small amount of secretions in a small tube can sharply increase the resistance to breathing.
- Tube-related emergencies, such as the tube coming out, happen more often in children than in adults.
- Babies need good humidification, because they lose a lot of fluid through fast breathing.
This doesn’t mean a tracheostomy is unsafe. Pediatric tracheostomy is performed regularly in specialist children’s hospitals. What it means is that the risk depends heavily on who’s caring for your baby every hour of the day. That’s true in ICU, and it is especially true at home.
The decision about whether the benefits outweigh the risks for your daughter is one for you and her treating team to make together. You have every right to ask questions, ask for time, and ask for a second or third opinion.
Next, will a tracheostomy affect my baby in the future? This is the question that keeps parents awake at night. Here’s what you need to know.
Voice and speech. With the tracheostomy, air goes in and out through the tube instead of the voice box, so your baby’s cry may sound different or be silent. When she’s ready, a speech pathologist may introduce a speaking valve, and allowing some air leak around the tube helps with sound production and speech development.
Feeding. Some babies need tube feeding for a while. The speech pathologist can assess her swallowing and help with oral feeding when it’s safe.
Development. Many babies with a tracheostomy can be more awake and active than with a breathing tube in the mouth, which can support development.
Removing the tracheostomy later. Many children do have their tracheostomy removed, decannulation, once the underlying problem has resolved and they no longer need it. Whether that’s possible for your daughter, and when, depends on the reason she needs it. Nobody can promise you a timeline.
The scar. There will usually be a small scar on the neck, which often fades as children grow.
Here’s the big picture. Your baby’s long-term outcome is mostly driven by the underlying condition, her lungs, her airway and her brain, not by the tracheostomy itself. That’s why it’s so important to understand exactly why she still needs breathing support.
So what questions should you ask the NICU or the PICU team before the tracheostomy? Here are some of the questions I’d encourage you to ask, so you ask the right questions:
1. What exactly is keeping my baby on the ventilator?
2. Has she had an echocardiogram recently, and is there still pulmonary hypertension?
3. Has she had an airway assessment, also known as a bronchoscopy, to check for narrowing or floppiness?
4. Has there been any neurological assessment, such as an MRI (Magnetic Resonance Imaging) or EEG (Electroencephalogram)?
5. How many extubation attempts have there been, and why did they fail?
6. What are the alternatives, and what happens if we wait?
7. Who will perform the surgery, and how many infant tracheostomies does this team do?
8. What’s the plan for weaning, and what’s the plan for going home?
9. What training will we get as parents? Do we need any, because I don’t really want to look after my baby’s tracheostomy?
We’ve put all of these, plus more, into our free Baby Tracheostomy Checklist. Download it in the show notes.
So why should you ask for your baby’s medical records? Families are generally speaking entitled to request access to their child’s health information. Ask the hospital’s health information or medical records department how to request your baby’s medical records. Do it now. Medical records give you the full picture: ventilator settings over time, blood gases, echocardiograms, imaging results, extubation attempts, neurological assessments, doctor’s notes, nursing notes, the notes from family meetings, fluid balance charts, medication charts, pathology results and ventilation charts. Leave no stone unturned.
With the medical records in your hand, or on an app, because that’s what it should be in 2026, it should just be on an app for you, ready to download, you can ask better questions, get an independent second opinion, and make informed decisions, instead of relying only on what you’re told at the bedside.
Next, can your baby with a tracheostomy and ventilator go home? In many, many cases, yes. Babies and children with a tracheostomy, with or without a ventilator, can and do live at home in Australia and around the world with 24/7 critical care registered nurses at home. Home ventilation has been established for decades now, mainly in countries like Germany, Austria and Australia.
According to our mechanical home ventilation guidelines, the right time to go home is when the underlying illness and any secondary illnesses are stable, funding for care is secured, and the necessary equipment, resources, materials and teams are in place.
For a ventilated baby, the equipment includes a ventilator suitable for infants, a second identical ventilator if ventilation is needed for more than 16 hours a day, an external battery, active humidification, a high-performance suction unit, a resuscitation bag, and spare tracheostomy tubes, including one size smaller for emergencies.
Your baby’s specialist pediatric team, pediatric intensivists, respiratory physicians and pediatricians, stays involved in her medical care. Intensive Care at Home works alongside them to provide the specialist nursing at home.
So who should actually look after a ventilated baby with a tracheostomy at home? I always compare it to flying an airplane. You wouldn’t board an airplane without a qualified pilot in the cockpit. A ventilated baby with a tracheostomy needs the equivalent of a pilot in the cockpit: a critical care registered nurse who can recognize a problem early and act immediately if the tube blocks or comes out.
Because let’s face it, you are now in ICU. You have critical care trained nurses, and that won’t change once your baby has a tracheostomy. So in order to go from ICU to home with a tracheostomy, you will also need 24/7 critical care registered nurses.
And you can look up, once again, our evidence-based mechanical ventilation guidelines. They set out the minimum qualifications for this kind of care, which means:
- The designated 24/7 specialist nurses managing the care need to be registered nurses with at least three years of intensive care or critical care nursing experience within the last five years, plus a postgraduate qualification in intensive care or critical care nursing, to oversee it.
- The nurses at the bedside providing day-to-day care need to be registered nurses with at least 18 months of intensive care or critical care nursing experience.
We have, if anything, upped the standard, not lowered it. We actually employ only ICU nurses with a minimum of two years ICU nursing experience. As a matter of fact, the average nurse on our books has 8 to 10 years of ICU or critical care nursing experience. That also means we are in a position to employ hundreds of years of ICU and critical care nursing experience combined in the community, which makes us the provider in Australia that brings the highest and strongest skill level into the community. When it comes to Intensive Care at Home, no other provider brings a higher skill level into the community than we do.
That gives you the opportunity to look after yourself. It gives you time to sleep, and maybe to look after other children and your spouse. With a ventilated baby, you shouldn’t have to carry the clinical responsibility 24 hours a day on your own. That’s why we provide Intensive Care at Home.
We’ve seen in Australia what can go wrong when the right skills aren’t there, in a case we’ve spoken about before. Noah Johnston, a ventilated person, had his tracheostomy tube become displaced in December last year, 2025, when no registered nurse was present, because the NDIS cut funding from 24/7 critical care registered nurses to only 12 hours a day. He was one of our clients, and he passed away when we were not there because of funding cuts, just as we and the family predicted at the time. But the NDIA (National Disability Insurance Agency) wasn’t listening, and therefore is responsible for Noah Johnston’s death. That’s exactly why we advocate so strongly for critical care nursing for anyone with a tracheostomy and a ventilator.
So how do we support babies and children at home with Intensive Care at Home? Well, Intensive Care at Home is, to our knowledge, the only third-party accredited Intensive Care at Home nursing service in Australia, accredited for Intensive Care at Home nursing. Our quality management system is certified to ISO (International Organization for Standardization) 9001:2015 for the delivery of intensive care nursing services at home, including services to ventilated patients and tracheostomy, and we are a registered NDIS provider. You can view our accreditation status on our website at intensivecareathome.com/accreditation-quality.
So what does that mean for your family?
- 24/7 ICU critical care registered nurses caring for babies and children with a tracheostomy on invasive ventilation, BiPAP non-invasive ventilation, or with a tracheostomy without ventilation.
- Discharge planning from NICU or PICU to home, working with your baby’s treating team. You can look up our discharge management page on our website.
- Home ventilation weaning in partnership with your baby’s medical team.
- Service all around Australia, in all states and territories.
Funding for a baby’s care at home can come from different sources, depending on your situation, such as state health and hospital programs, the NDIS, including the early childhood pathway for young children, private health insurance, or other schemes, including departments of health, etc. Eligibility and funding decisions are made by these bodies, not by us, but we can help you understand the options and what evidence is usually needed.
We’ve supported babies and children at home before, including a newborn baby. You can check out the show notes for a link to a case study, and also a medically complex ventilated toddler moving from hospital to home.
So talk to us about bringing your baby home. Call us on one of the numbers on the top of our website at intensivecareathome.com, or book a call with me by clicking on the schedule appointment button, or send me an email to [email protected]. Don’t forget to download your free Baby Tracheostomy Checklist.
The bottom line is this. A tracheostomy for a full-term baby after meconium aspiration is a big decision, but it’s often a step towards a more stable airway, more awake time, better development, and in many cases, going home. It is surgery, and it carries risk, especially in small babies, which is why the skill of the people caring for your baby every hour matters so much. Ask why your baby is still on the ventilator. Ask for her medical records. Ask about the plan for weaning and the plan for going home. And know that there is an alternative with Intensive Care at Home, as opposed to being in intensive care for weeks or months on end. Call us now at intensivecareathome.com.
Please remember that this video and article provide general information only and are not a substitute for advice from your baby’s treating medical team. Every baby’s situation is different. In an emergency, call triple zero (000).
A note on NDIS support coordination: where Intensive Care at Home provides NDIS support coordination, participants and their families are always free to choose any registered or unregistered provider for their nursing and other supports as well.
With all of that said, with Intensive Care at Home, we are currently sending our critical care nurses into the home 24 hours a day. Therefore, we are providing a genuine alternative to long-term stay in intensive care for:
- Ventilation
- Tracheostomy
- Home BiPAP (Bilevel Positive Airway Pressure), Home CPAP (Continuous Positive Airway Pressure) (https://intensivecareathome.com/quality-life-nursing-services-adults-children-requiring-non-invasive-mask-ventilation-cpap-bipap-andor-high-flow-oxygen-therapy/) ventilation without tracheostomy
- Tracheostomy care without ventilation
- Home TPN (https://intensivecareathome.com/tpntotal-parenteral-nutrition-administration-picc-line-central-line-care-community/)
- Home IV potassium
- Home IV magnesium
- Home IV antibiotics
- Home IV fluids
We’re providing:
- Cough assist management at home
- Ventilation weaning management at home
- Central line (http://intensivecarehotline.com/central-venous-lines/), PICC (Peripherally Inserted Central Catheter) line, Hickman’s line as well as port management at home
- Nasogastric tube, nasojejunostomy tube, PEG (Percutaneous Endoscopic Gastrostomy) (https://intensivecarehotline.com/your-loved-ones-treatment/peg-percutaneous-endoscopic-gastrostomy/), PEJ (Percutaneous Endoscopic Jejunostomy) tube management at home
- IDC (Indwelling Catheter) and SPC (Suprapubic Catheter) management at home
- Palliative care services at home
We’re also sending our critical care nurses into the home for emergency department bypass services. We have done so successfully as part of the Western Sydney Local Health District’s In Touch program, saving approximately $2,000 per patient that we keep at home instead of them going into an emergency department.
That also means we’re in a position to cut the cost of an ICU bed by around 50%. An intensive care bed costs between $5,000 to $10,000 per bed day depending on location. Intensive Care at Home costs approximately 50% of that, and we’re freeing up the most sought-after bed in the hospital, which is the ICU bed. Most importantly, we’re improving the quality of life for patients and their families, which is a win-win situation for all stakeholders.
Our Coverage and Accreditation
With Intensive Care at Home, we’re currently operating all around Australia, in all major capital cities, as well as in all regional and rural areas. We are an NDIS approved service provider all around Australia, TAC (Transport Accident Commission) and WorkSafe in Victoria as well as the Department of Veterans Affairs all around Australia.
We’re also ISO 9001:2015 accredited. Our clients and we as a service provider have also received funding through public hospitals, private health funds as well as departments of health.
We are the only service provider in Australia that has achieved third-party accreditation for Intensive Care at Home nursing in 2025. We have been achieving this high level of accreditation since 2012. No other provider in Australia has achieved the Intensive Care at Home level of accreditation in the community and has created more intellectual property when it comes to Intensive Care at Home nursing than we have.
This puts us in a position to employ hundreds of years of critical care nursing experience combined in the community. No other service provider in 2025 employs a higher skill level in the community than we do. And that enables us to look after the highest acuity adults and children in the community in Australia safely.
If You Need Help
If you’re at home already and you’re watching this or you’re stuck in an ICU and you realize that you don’t have the right level of support, I can give you many examples where we helped clients with funding, how we advocate for funding. We had to advocate successfully for funding from our first case study to many other case studies where we had to advocate successfully for funding with the right evidence of course because it is crystal clear that disability support workers for example or registered nurses without ICU experience cannot look after ventilated clients at home whether adults or children with or without a tracheostomy and it’s simply dangerous and negligent.
There are plenty of examples where clients with support worker models or even RN (registered nurse) models without ICU experience have died at home and I have evidence to back up everything that I’m saying here because it’s a bit like flying the airplane with a cabin crew instead of the pilot and it could simply be deadly.
This can be avoided by having simply 24-hour critical care nurses at home because our clients are at high risk of medical emergencies or worse without critical care nurses 24 hours. This is actually also evidence-based in the community and is documented in our evidence-based Mechanical Home Ventilation Guidelines on our website at intensivecareathome.com.
Think about it: in an intensive care unit in a hospital, you wouldn’t have support workers or general registered nurses looking after a critical care patient on a ventilator with a tracheostomy. So why would anyone in their right mind do that in a home care environment where there are fewer resources?
Clients that have found us have been at home long-term predictably and permanently with critical care nurses. Their alternative would have been to either die or stay in ICU long-term, and our clients don’t go back to ICU. They stay at home permanently and predictably and the insurance bodies save half of the cost of an ICU. But it’s a win-win situation all around.
We can do the same for you if you’re stuck in ICU or if you’re not safe at home, which includes the advocacy for funding and the network that goes along with it. We have always successfully advocated for our clients or we have the network to successfully advocate for you and for your family member, otherwise we wouldn’t be in business. The same again is applicable for those stuck in an ICU which is similar to many of our, if not most of our cases.
Our Support Coordination Services
This is also why we are providing Level 2 and Level 3 NDIS support coordination. We have a team of experienced NDIS support coordinators, and they have a wealth of knowledge. We’re also providing TAC case management and WorkSafe case management in Victoria with Lucy McCotter.
If you’re an NDIS support coordinator or a case manager or a social worker from another organization or a hospital watching this and you’re looking for nursing care for your participants, please reach out to us as well. If you’re looking for funding for nursing care for your participants and you don’t know how to go about it and how to advocate for it, what evidence to provide, I encourage you to reach out to us as well. We have the network to make that happen. We will help you with the right level of funding and with the right level of advocacy.
We’re also providing NDIS specialist nursing assessments done by critical care nurses with a legal nurse consulting background.
Join Our Team
If you are a critical care nurse and you’re looking for a career change and you want to join a very progressive, dynamic, successful, and high-performing team of critical care nurses in the community, we are employing hundreds of years of critical care nursing experience combined.
If you’re looking for a career change, we’re currently hiring for jobs for critical care nurses in Melbourne, Sydney, Brisbane, Albury-Wodonga, Bendigo, Geelong, Warragul, and also in Wyelangta in Victoria.
If you have worked in critical care nursing for a minimum of two years, adult ICU, pediatric ICU, ED and you have already completed a postgraduate critical care nursing qualification, we will be absolutely delighted hearing from you.
I have a disclaimer though: Because we are offering tailor-made solutions for our clients which includes regular staff, our clients do also want the same staff coming over and over again because they are so vulnerable and so special. That’s why we need regular, reliable staff.
If you’re looking for agency work where you can come and go, this will not be the right fit for you. We’re looking for consistency and our clients are looking for consistency. So please only apply with us if you can give us regular and consistent availabilities for shifts and you’re really keen on building relationships with us and with our clients. Reliability is also a must.
For Medical Professionals and Healthcare Executives
If you’re an intensive care specialist or an ED specialist, we also want to hear from you. We’re currently expanding our medical team as well.
We can also help you eliminate your bed blocks in your ICU and in your ED for your long-term patients or for your regularly readmitting patients with our critical care nursing team at home. We’re here to help to take the pressure off your ICU and ED beds. In most cases, you won’t even pay for it. Even if you do pay for it, it is so much more cost-effective than what you’re paying for in ICU and ED settings, and you get the same level of care and simply more patient and family satisfaction because you also want to partner with your consumers.
If you are a hospital executive watching this, we can help you free up your ICU and ED beds.
International Support
If you’re in the U.S. or in the UK and you’re watching this and you need help, we want to hear from you as well. We can help you there privately with one-on-one consulting and with hiring nurses privately.
Once again, our website is intensivecareathome.com. Call us on one of the numbers on the top of our website or simply send us an email to [email protected].
If you like my videos, click the like button, subscribe to my YouTube channel for regular updates for families with Intensive Care at Home and intensive care. Click the like button, click the notification bell, and share this video with anyone who has a family member in intensive care long-term or needs to see this.
Thank you so much for watching.
This is Patrik Hutzel from intensivecareathome.com and I’ll talk to you in a few days.
Take care for now.
RELATED LINKS:
 Why specialized services for Long-term ventilated adults and children with Tracheostomy outside of Intensive Care in the community are becoming a vital necessity!
INTENSIVE CARE AT HOME is it evidence based?
ARE INTENSIVE CARE UNITS OPERATING IN A VACUUM WHEN IT COMES TO END OF LIFE SITUATIONS?
Is looking after long-term ventilated Patients with tracheostomies in Intensive Care “best practice”?
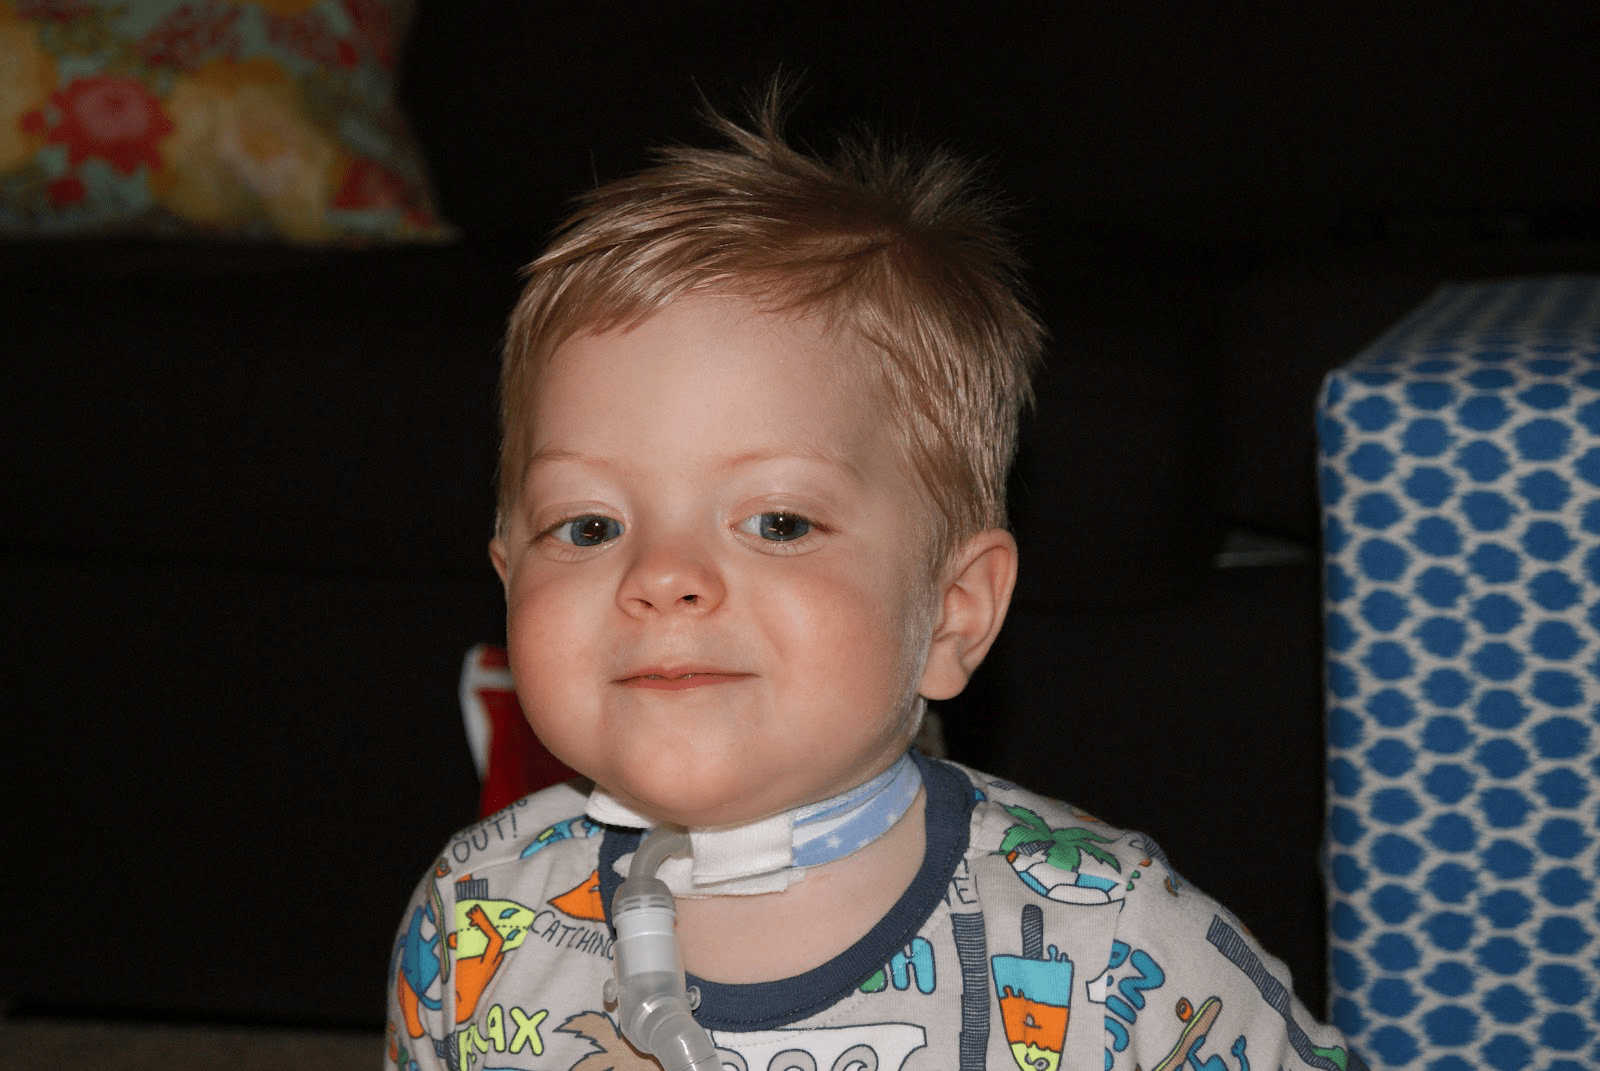 Freeing up hospital beds—how children can leave hospital sooner!

