


Podcast: Play in new window | Download
My name is Patrik Hutzel from intensivecareathome.com, where we provide tailor-made solutions for long-term ventilated adults and children with tracheostomy at home with 24/7 ICU and critical care trained nurses, where we provide tailor-made solutions for long-term ventilated adults and children on BiPAP (Bilevel Positive Airway Pressure), CPAP (Continuous Positive Airway Pressure) without tracheostomy with 24-hour critical care registered nurses at home, where we provide tailor-made solutions for adults and children with tracheostomies without ventilation with 24/7 critical care registered nurses and ICU nurses, where we provide home ventilation and home tracheostomy weaning when medically appropriate, where we provide home cough assist management. We provide home TPN (Total Parenteral Nutrition), IV (intravenous) fluids, IV antibiotics, IV potassium and magnesium, as well as central line, PICC (Peripherally Inserted Central Catheter) line, Hickman’s line and port management at home. We provide nasogastric tube, nasojejunostomy tube, PEG (Percutaneous Endoscopic Gastrostomy) and PEJ (Percutaneous Endoscopic Jejunostomy) tube management at home, as well as IDC (Indwelling Catheter) and SPC (Suprapubic Catheter) management at home, as well as palliative care management at home. We’re also providing Level 2 and Level 3 NDIS (National Disability Insurance Scheme) support coordination, as well as TAC (Transport Accident Commission) and WorkSafe case management.
Now, your loved one is in intensive care, maybe on a ventilator, maybe with a tracheostomy. And the question keeping you up at night is, how long does it actually take to get my family member home with Intensive Care at Home? In this video, I’m going to walk you through the eight steps from your first phone call to the first night at home, what may slow it down, and how you can speed it up. Stay with me.
Before we go on: if your loved one is in ICU right now and you want to talk about bringing them home, or you are at home already and you have insufficient support, call us now on one of the numbers on the top of our website at intensivecareathome.com, or click the schedule appointment button, or simply email me at [email protected]. And grab our free checklist. The link is in the description below, in the show notes. It lays out all eight steps so you can tick them off as you go.
So why does it take time to go home from ICU with Intensive Care at Home? In ICU, the ICU and the hospital provide everything: ventilator, suction, oxygen, doctors and intensive care nurses around the clock. When your loved one comes home, all of that has to be in place before they leave ICU or hospital.
I always compare it to a pilot in the cockpit. You wouldn’t let a plane take off without a trained pilot, a fueled aircraft and a flight plan. At home, the critical care nurse, or ICU nurse, is the pilot, the equipment is the aircraft, and the discharge plan is the flight plan. All three must be ready on the day.
Our evidence-based Mechanical Home Ventilation Guidelines spell this out. Discharge should happen when the condition is stable and when funding, equipment and resources are secured. I’ll put the link in the description.
So let’s now look at steps one and two: first call and assessment.
Step one, the first conversation. You pick up the phone or send an email to us, or you book a call with me by clicking the schedule appointment button. We want to understand the diagnosis, how long your loved one has been in ICU, ventilator or BiPAP, tracheostomy or not, and most importantly, what your loved one and your family want. That can happen the same day.
Step two, the clinical assessment. We need the clinical picture: discharge summary, ventilation settings, tracheostomy tube type and size, medications, nutrition, secretions. From there, a nursing assessment is prepared, and that is often the key document. A funding body needs to understand why critical care nursing is required. Usually this happens within the first week.
Step three, funding. That can be the step that takes the longest, but it doesn’t have to be. If it’s a private health fund or self-funded, it can be quick. Of course, TAC, WorkSafe and DVA (Department of Veterans’ Affairs) can often move a little bit quicker, depending on the claim. Private health insurance varies quite a bit, but can be very quick as well. And the NDIS can take a few weeks to months, especially if an NDIS plan needs to be reassessed, a decision reviewed, or a plan needs to be created from scratch.
If your loved one is over 65 and not eligible for the NDIS, it can be a little bit more difficult. But more difficult doesn’t mean impossible. It means you need to start early and explore every option, including Department of Health options.
Now, we can’t make the funding decisions, and we can’t exactly guarantee outcomes. What we can do is explain your options, prepare the clinical documentation, and work with your NDIS support coordinator, case manager, treating team, etc.
Just keep in mind, we’ve been doing Intensive Care at Home now since 2012, and there were no established funding pathways. The funding, however, is never the issue. We would not exist if the funding for our clients didn’t exist. So we can definitely help. We created funding streams for our clients out of thin air, where everybody told us, “Oh, no one will pay for that.” Well, picture this. The ICU bed costs $5,000 to $10,000 per bed day. We cut that cost by approximately 50%. Do you think that a funding body would have an interest in cutting the cost of the ICU bed by 50% and freeing up an ICU bed? I think you have the answer: they are interested. So if you don’t ask, you don’t get. That’s for sure.
Step four, equipment and the home. For someone on a ventilator with a tracheostomy, you’re typically looking at:
- A home ventilator, and a second identical one if they’re ventilated
- Backup batteries
- A heated humidifier
- Powerful, battery-operated suction units, at times two
- A resus bag with a tracheostomy adapter and PEEP (Positive End-Expiratory Pressure) valve
- Spare tracheostomy tubes, including one size smaller
- A suitable bed
And the home needs to be safe and accessible, with a decent power supply. The good news is equipment can be organized at the same time as funding and team building, often within one to three weeks.
Step five, building your CCRN (Critical Care Registered Nurse) nursing team. This is where we are different. Our guidelines say home ventilation must be provided by critical care trained nurses with at least 18 months of ICU experience. But our nurses have a minimum of two years ICU experience, because we keep our standards high. As a matter of fact, we employ hundreds of years of critical care registered nursing experience combined. The average experience for our nurses is probably more like 8 to 10 years, and around 75% of our nurses are critical care trained, similar to an ICU. So we’re not making it up when we say Intensive Care at Home, because that’s exactly what we are.
And the nurse leading the care for a team should have at least five years of recent ICU experience, plus a postgraduate intensive care nursing qualification.
For a 24-hour roster, which is necessary when you go home from ICU, you need at least 10 nurses, plus backup. In the cities, that can often come together in a few days or weeks. Regionally and remotely, it can take longer, but we’ll always tell you up front what’s realistic and how quickly we can move.
Step six, orientation. Wherever the hospital allows it, our ICU nurses meet your loved one in ICU before discharge, starting with learning your loved one’s routine and settings.
Step number seven, the discharge planning meeting and discharge day. Everyone around the table agrees on the plan and on the day. The nurse is there from the moment your loved one gets home.
Step eight, the first 72 hours. Close monitoring, documentation every shift, close contact with the treating doctors, and from there, regular reviews and, where it’s medically appropriate, goals like weaning at home.
Next, what slows it down and how to speed it up. So what actually slows a transition home from ICU with Intensive Care at Home? Funding might be delayed sometimes, but more often than not, it’s starting the process too late, missing documentation, equipment lead times, sometimes medical instability in ICU, and sometimes disagreements between the hospital, the funding body and the family about what care is needed.
How do you speed it up?
- Start planning early, while your loved one is still in ICU.
- Run the steps in parallel, not one after the other.
- Ask the treating team for their support letters.
- Ask for a discharge planning meeting early.
For the NDIS, for example, you will also need doctor’s letters, a nursing assessment, a physiotherapy assessment, a functional capacity assessment from the OT (Occupational Therapist), and sometimes a speech therapy assessment as well.
That’s why it’s so important that you get the medical records. You can usually request them through the hospital’s health information or freedom of information process. Ask for the discharge summary, ventilator settings, tracheostomy details, nursing notes and allied health reports. Medical records give you information, and information gives you control, power and influence.
Next, accreditation and Intensive Care at Home services. When you’re choosing a provider, ask about third-party accreditation. In 2026, and as far as I’m aware, Intensive Care at Home is the only third-party accredited Intensive Care at Home nursing service in Australia, accredited for Intensive Care at Home nursing. Our quality management system is certified to ISO (International Organization for Standardization) 9001:2015, as well as NDIS standards, so we are NDIS registered. The link to our certificates is in the show notes. We work with NDIS, TAC, WorkSafe, DVA, private health funds, departments of health, hospitals and private clients, right across Australia, in all states and territories.
So how long does it take to set up Intensive Care at Home? It depends a little bit, but you have more influence and more options over that timeline than you think. Start early, run things in parallel, get the medical records, reach out to us on day one, and work with a team that knows how to do this safely.
If your loved one is in ICU right now, or you’re at home already and you don’t have enough support, call us at intensivecareathome.com on one of the numbers on the top of our website, or click the schedule appointment button and book a call with me, or simply call me on my mobile phone, 041 094 2230, or simply email me at [email protected].
If you’re in the US, Canada, UK, India, anywhere around the world, and you are interested in Intensive Care at Home, please reach out to us as well through our website. There are international phone numbers there as well. And download the free checklist below. And if this video helped you, subscribe and hit the bell so you don’t miss the next one. Leave your questions in the comments so I can answer them in a future video. Take care.
About Intensive Care at Home
With all of that said, with Intensive Care at Home, we are currently sending our critical care nurses into the home 24 hours a day. Therefore, we are providing a genuine alternative to long-term stay in intensive care for:
- Ventilation
- Tracheostomy
- Home BiPAP (Bilevel Positive Airway Pressure), Home CPAP (Continuous Positive Airway Pressure) (https://intensivecareathome.com/quality-life-nursing-services-adults-children-requiring-non-invasive-mask-ventilation-cpap-bipap-andor-high-flow-oxygen-therapy/) ventilation without tracheostomy
- Tracheostomy care without ventilation
- Home TPN (https://intensivecareathome.com/tpntotal-parenteral-nutrition-administration-picc-line-central-line-care-community/)
- Home IV potassium
- Home IV magnesium
- Home IV antibiotics
- Home IV fluids
We’re providing:
- Cough assist management at home
- Ventilation weaning management at home
- Central line (http://intensivecarehotline.com/central-venous-lines/), PICC (Peripherally Inserted Central Catheter) line, Hickman’s line as well as port management at home
- Nasogastric tube, nasojejunostomy tube, PEG (Percutaneous Endoscopic Gastrostomy) (https://intensivecarehotline.com/your-loved-ones-treatment/peg-percutaneous-endoscopic-gastrostomy/), PEJ (Percutaneous Endoscopic Jejunostomy) tube management at home
- IDC (Indwelling Catheter) and SPC (Suprapubic Catheter) management at home
- Palliative care services at home
We’re also sending our critical care nurses into the home for emergency department bypass services. We have done so successfully as part of the Western Sydney Local Health District’s In Touch program, saving approximately $2,000 per patient that we keep at home instead of them going into an emergency department.
That also means we’re in a position to cut the cost of an ICU bed by around 50%. An intensive care bed costs between $5,000 to $10,000 per bed day depending on location. Intensive Care at Home costs approximately 50% of that, and we’re freeing up the most sought-after bed in the hospital, which is the ICU bed. Most importantly, we’re improving the quality of life for patients and their families, which is a win-win situation for all stakeholders.
Our Coverage and Accreditation
With Intensive Care at Home, we’re currently operating all around Australia, in all major capital cities, as well as in all regional and rural areas. We are an NDIS approved service provider all around Australia, TAC (Transport Accident Commission) and WorkSafe in Victoria as well as the Department of Veterans Affairs all around Australia.
We’re also ISO 9001:2015 accredited. Our clients and we as a service provider have also received funding through public hospitals, private health funds as well as departments of health.
We are the only service provider in Australia that has achieved third-party accreditation for Intensive Care at Home nursing in 2025. We have been achieving this high level of accreditation since 2012. No other provider in Australia has achieved the Intensive Care at Home level of accreditation in the community and has created more intellectual property when it comes to Intensive Care at Home nursing than we have.
This puts us in a position to employ hundreds of years of critical care nursing experience combined in the community. No other service provider in 2025 employs a higher skill level in the community than we do. And that enables us to look after the highest acuity adults and children in the community in Australia safely.
If You Need Help
If you’re at home already and you’re watching this or you’re stuck in an ICU and you realize that you don’t have the right level of support, I can give you many examples where we helped clients with funding, how we advocate for funding. We had to advocate successfully for funding from our first case study to many other case studies where we had to advocate successfully for funding with the right evidence of course because it is crystal clear that disability support workers for example or registered nurses without ICU experience cannot look after ventilated clients at home whether adults or children with or without a tracheostomy and it’s simply dangerous and negligent.
There are plenty of examples where clients with support worker models or even RN (registered nurse) models without ICU experience have died at home and I have evidence to back up everything that I’m saying here because it’s a bit like flying the airplane with a cabin crew instead of the pilot and it could simply be deadly.
This can be avoided by having simply 24-hour critical care nurses at home because our clients are at high risk of medical emergencies or worse without critical care nurses 24 hours. This is actually also evidence-based in the community and is documented in our evidence-based Mechanical Home Ventilation Guidelines on our website at intensivecareathome.com.
Think about it: in an intensive care unit in a hospital, you wouldn’t have support workers or general registered nurses looking after a critical care patient on a ventilator with a tracheostomy. So why would anyone in their right mind do that in a home care environment where there are fewer resources?
Clients that have found us have been at home long-term predictably and permanently with critical care nurses. Their alternative would have been to either die or stay in ICU long-term, and our clients don’t go back to ICU. They stay at home permanently and predictably and the insurance bodies save half of the cost of an ICU. But it’s a win-win situation all around.
We can do the same for you if you’re stuck in ICU or if you’re not safe at home, which includes the advocacy for funding and the network that goes along with it. We have always successfully advocated for our clients or we have the network to successfully advocate for you and for your family member, otherwise we wouldn’t be in business. The same again is applicable for those stuck in an ICU which is similar to many of our, if not most of our cases.
Our Support Coordination Services
This is also why we are providing Level 2 and Level 3 NDIS support coordination. We have a team of experienced NDIS support coordinators, and they have a wealth of knowledge. We’re also providing TAC case management and WorkSafe case management in Victoria with Lucy McCotter.
If you’re an NDIS support coordinator or a case manager or a social worker from another organization or a hospital watching this and you’re looking for nursing care for your participants, please reach out to us as well. If you’re looking for funding for nursing care for your participants and you don’t know how to go about it and how to advocate for it, what evidence to provide, I encourage you to reach out to us as well. We have the network to make that happen. We will help you with the right level of funding and with the right level of advocacy.
We’re also providing NDIS specialist nursing assessments done by critical care nurses with a legal nurse consulting background.
Join Our Team
If you are a critical care nurse and you’re looking for a career change and you want to join a very progressive, dynamic, successful, and high-performing team of critical care nurses in the community, we are employing hundreds of years of critical care nursing experience combined.
If you’re looking for a career change, we’re currently hiring for jobs for critical care nurses in Melbourne, Sydney, Brisbane, Albury-Wodonga, Bendigo, Geelong, Warragul, and also in Wyelangta in Victoria.
If you have worked in critical care nursing for a minimum of two years, adult ICU, pediatric ICU, ED and you have already completed a postgraduate critical care nursing qualification, we will be absolutely delighted hearing from you.
I have a disclaimer though: Because we are offering tailor-made solutions for our clients which includes regular staff, our clients do also want the same staff coming over and over again because they are so vulnerable and so special. That’s why we need regular, reliable staff.
If you’re looking for agency work where you can come and go, this will not be the right fit for you. We’re looking for consistency and our clients are looking for consistency. So please only apply with us if you can give us regular and consistent availabilities for shifts and you’re really keen on building relationships with us and with our clients. Reliability is also a must.
For Medical Professionals and Healthcare Executives
If you’re an intensive care specialist or an ED specialist, we also want to hear from you. We’re currently expanding our medical team as well.
We can also help you eliminate your bed blocks in your ICU and in your ED for your long-term patients or for your regularly readmitting patients with our critical care nursing team at home. We’re here to help to take the pressure off your ICU and ED beds. In most cases, you won’t even pay for it. Even if you do pay for it, it is so much more cost-effective than what you’re paying for in ICU and ED settings, and you get the same level of care and simply more patient and family satisfaction because you also want to partner with your consumers.
If you are a hospital executive watching this, we can help you free up your ICU and ED beds.
International Support
If you’re in the U.S. or in the UK and you’re watching this and you need help, we want to hear from you as well. We can help you there privately with one-on-one consulting and with hiring nurses privately.
Once again, our website is intensivecareathome.com. Call us on one of the numbers on the top of our website or simply send us an email to [email protected].
If you like my videos, click the like button, subscribe to my YouTube channel for regular updates for families with Intensive Care at Home and intensive care. Click the like button, click the notification bell, and share this video with anyone who has a family member in intensive care long-term or needs to see this.
Thank you so much for watching.
This is Patrik Hutzel from intensivecareathome.com and I’ll talk to you in a few days.
Take care for now.
RELATED LINKS:
 Why specialized services for Long-term ventilated adults and children with Tracheostomy outside of Intensive Care in the community are becoming a vital necessity!
INTENSIVE CARE AT HOME is it evidence based?
ARE INTENSIVE CARE UNITS OPERATING IN A VACUUM WHEN IT COMES TO END OF LIFE SITUATIONS?
Is looking after long-term ventilated Patients with tracheostomies in Intensive Care “best practice”?
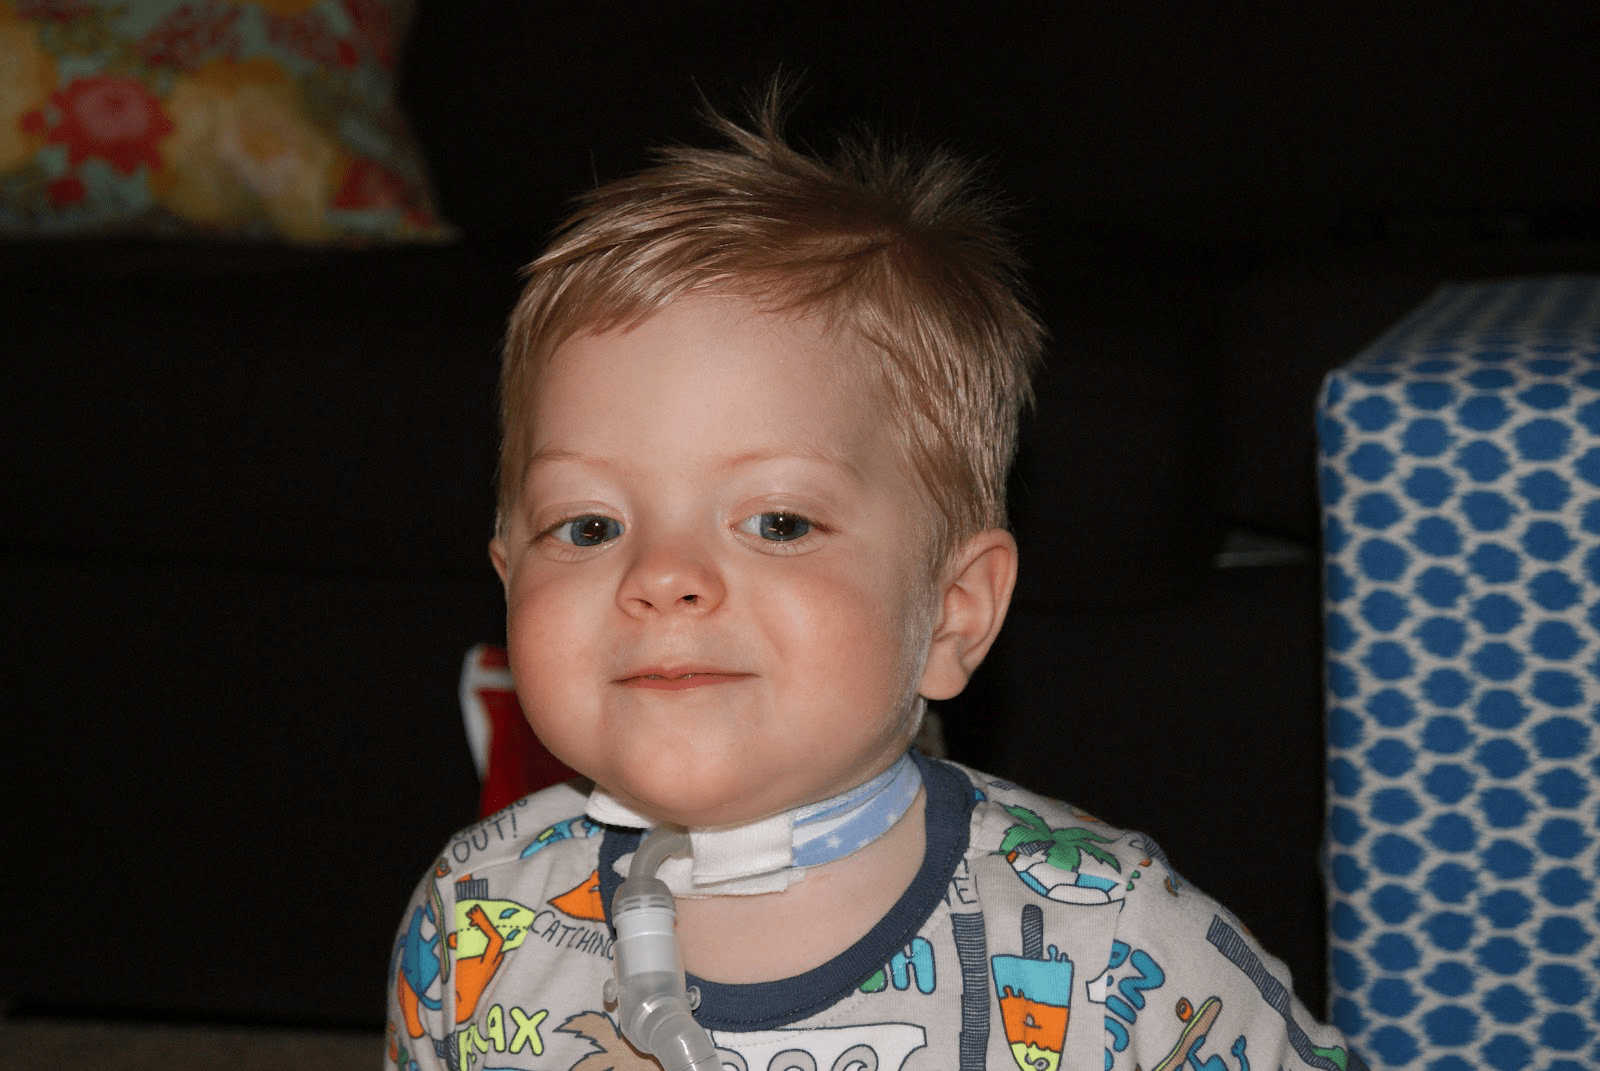 Freeing up hospital beds—how children can leave hospital sooner!

